

Receiving a pelvic ultrasound report that notes a "bulky uterus" can feel alarming. Many women immediately worry about serious reproductive illnesses, tumors, or permanent infertility. However, in clinical practice, a bulky uterus is not an independent disease or a cancer diagnosis; rather, it is a descriptive radiological finding indicating that your uterus has expanded beyond its standard baseline dimensions.
While an enlarged uterus naturally expands up to 20 times its original size during pregnancy to accommodate a growing baby, non-pregnant enlargement occurs when the uterine muscular walls (myometrium), connective tissues, or inner mucosal lining (endometrium) expand due to benign reproductive conditions.
The two most common clinical culprits behind a bulky uterus are uterine fibroids (leiomyomas) and adenomyosis. While rarely life-threatening, these conditions can cause debilitating symptoms—including heavy, painful menstrual bleeding, chronic pelvic fullness, and recurrent implantation failure during natural conception or In Vitro Fertilization (IVF).
In this definitive guide, senior reproductive endocrinologists and gynecological specialists at Progenesis Fertility Center break down what constitutes normal uterine dimensions in millimeters, why a uterus becomes bulky, key symptom waing signs, how it impacts natural conception and IVF, and the most advanced, uterus-sparing treatments available today.
What is a Bulky Uterus? Normal Size vs Enlarged Dimensions
In an adult woman of reproductive age who has never been pregnant (nulliparous), a healthy uterus is a hollow, pear-shaped pelvic organ situated between the urinary bladder and the rectum. Its anatomical dimensions are measured accurately across three axes using high-resolution transvaginal ultrasound (TVS) or pelvic MRI:
- Length (Cervix to Fundus): Typically 70 mm to 80 mm (7 to 8 cm).
- Width (Transverse Diameter): Typically 40 mm to 50 mm (4 to 5 cm).
- Anteroposterior (AP) Thickness: Typically 25 mm to 35 mm (2.5 to 3.5 cm).
- Total Weight: Approximately 50 to 70 grams (volume of 40 to 80 cm³).
When one or more of these measurements increase—especially when uterine length exceeds 85 mm to 90 mm or weight surpasses 100 to 120 grams outside of active pregnancy—radiologists designate the organ as a bulky uterus.
Clinical Fact: Mild uterine enlargement is often a normal physiological adaptation in women who have delivered multiple children (multiparity). However, when accompanied by heavy periods, severe cramps, or fertility challenges, it warrants targeted clinical evaluation.
Uterine Dimensions Matrix: Normal vs Bulky Uterus
| Clinical Category | Length (mm / cm) | Width (mm / cm) | AP Thickness (mm / cm) | Estimated Weight | Typical Clinical Status |
|---|---|---|---|---|---|
| Normal Nulliparous (Never Pregnant) | 70–80 mm (7–8 cm) | 40–50 mm (4–5 cm) | 25–30 mm (2.5–3 cm) | 50–70 g | Healthy reproductive baseline. |
| Normal Multiparous (Prior Deliveries) | 80–90 mm (8–9 cm) | 50–60 mm (5–6 cm) | 30–35 mm (3–3.5 cm) | 70–90 g | Physiological post-pregnancy remodeling. |
| Postmenopausal Baseline | 50–65 mm (5–6.5 cm) | 25–35 mm (2.5–3.5 cm) | 15–25 mm (1.5–2.5 cm) | 30–40 g | Normal physiological atrophy due to low estrogen. |
| Mild Bulky Uterus | 85–100 mm (8.5–10 cm) | 55–65 mm (5.5–6.5 cm) | 35–45 mm (3.5–4.5 cm) | 100–140 g | Early adenomyosis, small intramural fibroids, multiparity. |
| Moderate to Severe Bulky Uterus | > 100–140+ mm (>10–14 cm) | > 70–90+ mm (>7–9 cm) | > 50–70+ mm (>5–7 cm) | 150–500+ g | Multiple large fibroids, extensive diffuse adenomyosis. |
Also Read: Endometrial Thickness: Normal Range, IVF Success & Treatment
Primary Clinical Causes of a Bulky Uterus
A bulky uterus is a secondary response to hormonal stimulation, cellular displacement, or localized tissue growth. Understanding the exact underlying pathology is essential for choosing the right treatment—especially if you are planning to conceive.
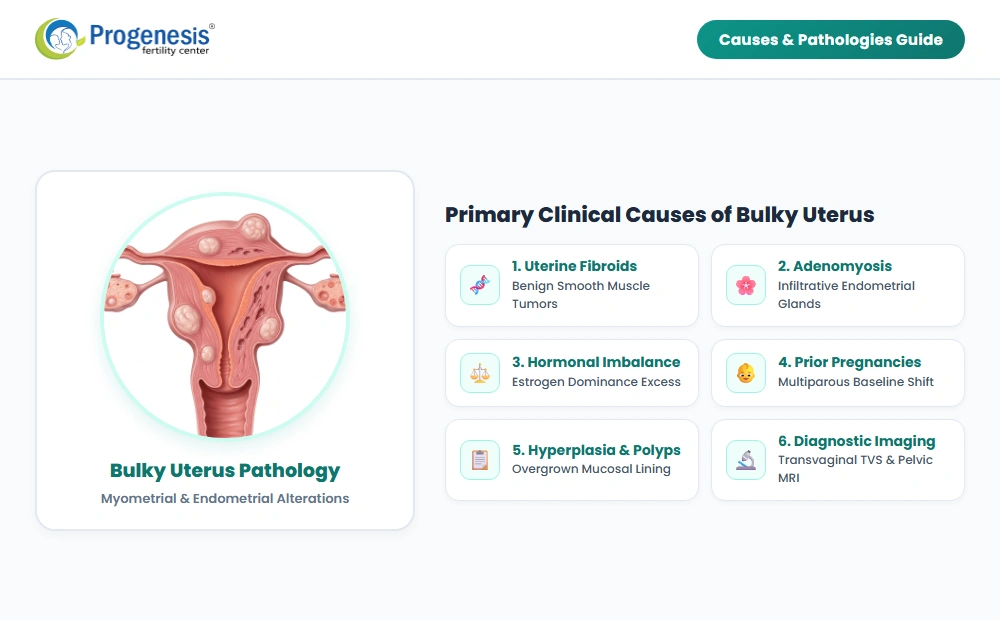
1. Uterine Fibroids (Leiomyomas)
Uterine fibroids are benign monoclonal tumors originating from the smooth muscle cells of the uterine wall (myometrium). Up to 70% to 80% of women develop fibroids by age 50. Depending on their anatomical position, fibroids can dramatically alter uterine contours:
* Submucosal Fibroids (Inside Cavity): Grow directly undeeath the uterine lining. Even small submucosal fibroids can cause intense menorrhagia and prevent embryo implantation.
* Intramural Fibroids (Inside Muscle Wall): Grow within the muscular wall, contributing significantly to a globally expanded, heavy uterus.
* Subserosal Fibroids (Outside Uterine Wall): Project outward into the pelvic cavity, exerting direct pressure on the bladder or rectum.
2. Adenomyosis (Endometrial Infiltration)
In adenomyosis, the glandular cells and stroma that normally line the interior uterine cavity break through the basement membrane and burrow deep into the surrounding myometrial muscle. With each monthly menstrual cycle, this trapped tissue thickens, breaks down, and bleeds inside the uterine muscle, triggering reactive hypertrophy (muscle thickening).
* Ultrasound Characteristics: Creates a globular, symmetrically enlarged "spongy" uterus with asymmetrical myometrial thickening and loss of the junctional zone definition.
* Peak Incidence: Most commonly diagnosed in women aged 35 to 50 and those undergoing fertility treatments.
3. Hormonal Imbalances (Estrogen Dominance)
Both the endometrium and myometrium are hyper-sensitive to reproductive hormones. In conditions characterized by chronic unopposed estrogen—such as Polycystic Ovary Syndrome (PCOS), obesity, or perimenopausal anovulation—persistent estrogen stimulation fuels muscle proliferation and mucosal overgrowth, leading to uterine bulkiness.
4. Multiparity (Multiple Past Pregnancies)
During pregnancy, the uterine muscle fibers undergo both hypertrophy (enlargement) and hyperplasia (multiplication). Following childbirth, the uterus undergoes involution, shrinking back down over 6 to 8 weeks. However, after multiple full-term pregnancies, the uterus rarely retus to its original virgin dimensions, frequently resting at an asymptomatic, mildly bulky baseline.
5. Endometrial Hyperplasia & Uterine Polyps
Endometrial hyperplasia is an abnormal thickening of the endometrial mucosal layer caused by excess estrogen without sufficient balancing progesterone. When combined with intracavitary polyps (fleshy benign growths), it increases overall uterine dimensions and poses a significant risk of irregular uterine bleeding.
6. Rare Causes (Pelvic Congestion & Malignancy)
- Pelvic Congestion Syndrome: Chronic retrograde blood pooling in engorged pelvic veins can cause secondary uterine enlargement and continuous pelvic ache.
- Uterine Sarcomas & Endometrial Carcinoma: While the overwhelming majority of bulky uteri are benign, rapid postmenopausal enlargement or atypical vascular pattes on Doppler scans require urgent biopsy to rule out malignant transformation.
Comparison: Adenomyosis vs Uterine Fibroids
| Clinical Parameter | Adenomyosis (Endometrial Infiltration) | Uterine Fibroids (Leiomyomas) |
|---|---|---|
| Pathology | Diffuse infiltration of endometrial glands into myometrium. | Well-circumscribed, encapsulated benign smooth muscle tumors. |
| Uterine Shape on Ultrasound | Uniformly enlarged, globular, soft, and symmetrical. | Irregular, asymmetric, nodular, and firm to palpation. |
| Primary Bleeding Pattern | Heavy, prolonged cycles with intense menstrual cramping. | Heavy menstrual bleeding with large clots, gushing, or spotting. |
| Pain Manifestation | Progressive secondary dysmenorrhea and deep dyspareunia (painful sex). | Localized dull pelvic ache, pressure, and backache from nerve compression. |
| Ultrasound Sign | "Venetian blind" acoustic shadowing, myometrial cysts, thickened junctional zone (>12 mm on MRI). | Distinct hypoechoic round masses with clear acoustic borders. |
| Impact on IVF | High: Impairs uterine peristalsis and induces chronic inflammatory cytokines. | Variable: High impact if distorting cavity (submucosal); moderate if large intramural. |
Also Read: Understanding Adenomyosis: Symptoms, Causes, and Treatment
Symptoms and Waing Signs of a Bulky Uterus
Many women with a mildly bulky uterus remain completely asymptomatic, discovering the condition incidentally during a routine annual female fertility check or prenatal scan. However, when enlargement progresses, it produces noticeable physical and systemic symptoms.

Key Symptom Categories:
- Abnormal Menstrual Bleeding (Menorrhagia):
- Periods lasting longer than 7 days.
- Bleeding so heavy that you soak through one or more sanitary pads or tampons every hour for consecutive hours.
- Passing dark, jelly-like blood clots larger than a quarter.
-
Unexplained spotting or breakthrough bleeding between cycles.
-
Severe Menstrual Cramping (Secondary Dysmenorrhea):
- Unlike standard teenage period cramps, bulky uterus pain often worsens with age.
- Cramping begins several days before bleeding starts and lingers well after flow finishes.
-
Pain radiates across the lower pelvis, deep lumbar spine, buttocks, and upper thighs.
-
Pelvic Heaviness, Abdominal Bloating & "Bulky Belly":
- Sensation of fullness or dragging heaviness in the lower pelvis.
-
Abdominal distension that causes pants, skirts, or waistbands to feel uncomfortably tight even without dietary weight gain.
-
Compromised Bladder and Bowel Function:
-
Because the enlarging uterus presses directly against neighboring pelvic organs:
- Bladder Compression: Frequent need to urinate, waking up multiple times at night (nocturia), sudden urinary urgency, or difficulty emptying the bladder completely.
- Rectal Compression: Chronic constipation, painful bowel movements, and chronic rectal pressure.
-
Deep Pain During Intercourse (Dyspareunia):
-
Deep pelvic aching or sharp discomfort during or immediately following sexual intimacy, frequently seen in cases of severe adenomyosis or retroverted bulky uteri.
-
Fatigue & Iron-Deficiency Anemia:
- Chronic excessive blood loss depletes systemic iron stores, resulting in persistent exhaustion, lightheadedness, shortness of breath on exertion, brittle nails, and pale skin.
Can You Get Pregnant with a Bulky Uterus? Natural Conception & IVF
One of the most pressing questions women ask our fertility specialists is: "Can I get pregnant if my ultrasound report says bulky uterus?"
The short answer is yes—many women conceive naturally and carry healthy pregnancies with a mildly bulky uterus. However, your pregnancy chances depend entirely on what is causing the enlargement, its location, and its severity.
How a Bulky Uterus Affects Fertility
When a bulky uterus is driven by significant adenomyosis or cavity-distorting fibroids, it creates several physiological roadblocks to conception:
┌────────────────────────────────────────────────────────┐ │ HOW A BULKY UTERUS IMPAIRS EMBRYO CONCEPTION │ └──────────────────────────┬─────────────────────────────┘ │ ┌───────────────────┼───────────────────┐ ▼ ▼ ▼ ┌──────────────┐ ┌──────────────┐ ┌──────────────┐ │ Anatomical │ │ Uterine Bed │ │ Biochemical │ │ Obstruction │ │ Peristalsis │ │ Inflammation │ └──────┬───────┘ └──────┬───────┘ └──────┬───────┘ │ │ │ ▼ ▼ ▼ Cavity distortion Abnormal muscle Overproduction of blocks sperm and contractions expel free radicals, prevents embryo sperm or disrupt TNF-α & IL-6 reduce attachment. blastocyst landing. endometrial receptivity. - Impaired Endometrial Receptivity: Adenomyotic tissue and submucosal fibroids downregulate critical implantation markers, such as HOXA10, leukemia inhibitory factor (LIF), and αvβ3 integrins, reducing the uterine lining’s biological receptivity.
- Disrupted Uterine Peristalsis: A healthy uterus exhibits gentle, rhythmic contractions that guide sperm upward toward the fallopian tubes. Diffuse adenomyosis causes irregular, hyperactive myometrial contractions (hyperperistalsis) that hinder sperm transport.
- Chronic Pelvic Inflammation: The presence of displaced endometrial glands in the myometrium generates elevated levels of inflammatory cytokines, prostaglandins, and reactive oxygen species (ROS) toxic to delicate embryos.
- Elevated Miscarriage and Obstetric Risks: If an embryo successfully implants in a significantly bulky, fibroid-dense uterus, the altered blood flow increases the risk of early miscarriage, fetal growth restriction (IUGR), placental abruption, and preterm labor.
IVF Protocols for Bulky Uterus: The Progenesis Approach
At Progenesis Fertility Center, having a bulky uterus does not mean your IVF jouey cannot succeed. Our reproductive endocrinologists utilize targeted preparation protocols:
- Downregulation with GnRH Agonists (Ultra-Long Protocol): Administering Depot Leuprolide acetate or Goserelin for 2 to 3 months prior to embryo transfer temporarily suppresses ovarian estrogen. This "quiets" the uterus, shrinks adenomyotic lesions, reduces overall uterine volume by 30% to 50%, and restores endometrial receptivity.
- Frozen Embryo Transfer (FET): Rather than performing a fresh transfer in an inflamed cycle, embryos are cultured to day-5 blastocysts and safely vitrified. The patient’s uterus is then carefully prepared in a controlled hormonal cycle (HRT-FET) following downregulation.
- Laparoscopic / Hysteroscopic Myomectomy: Submucosal fibroids distorting the cavity or large intramural fibroids (>4 to 5 cm) are surgically excised before initiating IVF to provide a pristine uterine cavity.
Also Read: Everything You Need to Know About IVF Treatment & Success Rates
Diagnostic Evaluation: How a Bulky Uterus is Confirmed
Accurate differentiation between adenomyosis, fibroids, and physiological enlargement requires specialized imaging:
- Bimanual Pelvic Examination: A gynecologist gently palpates the abdomen and pelvic organs. An enlarged, tender, globular uterus indicates potential adenomyosis, whereas an irregularly contoured, firm, non-tender mass suggests uterine fibroids.
- High-Resolution Transvaginal Ultrasound (TVS): The primary first-line modality. TVS enables doctors to measure uterine length, width, and AP thickness, evaluate myometrial texture, assess the endometrial stripe, and detect localized tumors.
- Pelvic 3D Ultrasound & Sonohysterography (SIS): Sterile saline is infused into the uterine cavity during sonography to clearly outline whether fibroids or polyps protrude into the endometrial lumen.
- Pelvic MRI (Magnetic Resonance Imaging): The gold standard for complex diagnostic dilemmas. MRI provides exceptional tissue contrast to clearly measure the uterine junctional zone (JZ). A JZ thickness exceeding 12 mm is pathognomonic for adenomyosis.
- Endometrial Biopsy: In women over 35 experiencing abnormal uterine bleeding or thickened endometrium, a fine catheter (Pipelle) extracts a small lining sample to rule out hyperplasia or malignancy before starting hormonal therapy.
Modern Treatment Options for Bulky Uterus
Treatment for a bulky uterus is never one-size-fits-all. Therapeutic strategy depends strictly on your symptom severity, underlying cause, age, and whether you wish to preserve your fertility.
Treatment Pathway by Clinical Goal
| Clinical Goal | Recommended Treatment Options | Expected Outcome & Benefits |
|---|---|---|
| Active Fertility & Pregnancy | • GnRH-agonist downregulation (Lupron depot) • Laparoscopic or robotic myomectomy • Hysteroscopic resection of submucosal fibroids • Controlled FET (Frozen Embryo Transfer) cycles | Shrinks uterine bulk, normalizes uterine cavity, resolves inflammation, maximizes embryo implantation success. |
| Symptom Relief (Fertility Complete) | • Levonorgestrel-releasing IUD (Mirena) • Uterine Artery Embolization (UAE) • Endometrial ablation • Oral progestins or combined contraceptives | Dramatically reduces heavy bleeding, alleviates cramps, avoids major abdominal surgery. |
| Definitive Cure (Severe Symptoms) | • Total Laparoscopic Hysterectomy (TLH) • Vaginal or abdominal hysterectomy | 100% permanent resolution of bleeding, pain, and uterine bulk. Ovaries are preserved when healthy to avoid surgical menopause. |
1. Medical & Hormonal Therapies
- Non-Hormonal Symptom Relief:
- Tranexamic Acid: An antifibrinolytic taken during cycle days reduces menstrual blood loss by up to 50% without altering hormones.
- NSAIDs (Mefenamic Acid / Ibuprofen): Inhibit excessive prostaglandin production, curbing severe pelvic cramps and reducing menstrual flow.
- Hormonal Management:
- Levonorgestrel IUD (Mirena): Delivers continuous localized progestin into the uterine cavity, thinning the endometrium and reducing heavy menstrual bleeding by over 80% to 90%. Excellent for adenomyosis in patients not immediately seeking pregnancy.
- Oral Progestins & Combined Oral Contraceptives: Regulate unpredictable menstrual cycles and manage dysmenorrhea.
- GnRH Agonists and Antagonists (e.g., Lupron, Relugolix): Induce a temporary, reversible menopausal state, substantially shrinking fibroids and calming adenomyosis tissue prior to planned surgery or IVF.
2. Minimally Invasive & Uterus-Sparing Procedures
- Hysteroscopic Resection: Under gentle sedation, a slim camera (hysteroscope) enters the uterus via the cervix to shave away cavity-distorting submucosal fibroids or polyps with zero abdominal incisions.
- Laparoscopic / Robotic Myomectomy: Surgical excision of intramural and subserosal fibroids through tiny 5–10 mm keyhole abdominal incisions, preserving the uterus for future pregnancy.
- Uterine Artery Embolization (UAE): A radiologist injects microscopic embolic particles into the uterine arteries, starving fibroids of blood supply and causing them to shrink by 40% to 60%. (Note: Typically recommended for women who have completed their families due to potential impact on ovarian blood supply).
- High-Intensity Focused Ultrasound (HIFU): Non-invasive thermal ablation using targeted acoustic energy under MRI guidance to destroy localized fibroids or focal adenomyomas.
3. Definitive Surgical Care: Hysterectomy
In women with incapacitating pain, severe chronic anemia, completed childbearing, or failed medical treatments, surgical removal of the uterus (hysterectomy) provides a permanent, definitive cure. Modern hysterectomies are performed laparoscopically or vaginally, requiring only a 1-day hospital stay and a rapid 2-week recovery. In premenopausal women, the ovaries are routinely preserved to protect natural hormone production and prevent early menopause.
4. Holistic Lifestyle & Dietary Support
While diet cannot dissolve established fibroids or adenomyosis, an anti-inflammatory lifestyle supports hormonal equilibrium and calms pelvic symptoms:
* Promote Estrogen Metabolism: Emphasize cruciferous vegetables (broccoli, cauliflower, Brussels sprouts) containing indole-3-carbinol, high-fiber legumes, and ground flaxseeds.
* Anti-Inflammatory Nutrition: Incorporate cold-water omega-3 fatty acids (salmon, chia seeds, walnuts), leafy greens, turmeric, and green tea to lower systemic prostaglandin production.
* Limit Endocrine Disruptors: Reduce exposure to environmental xenoestrogens by minimizing processed foods, red meats, alcohol, and heating foods in plastic containers.
* Maintain Healthy Body Composition: Adipose tissue contains the enzyme aromatase, which converts androgens into extra estrogen. Sustaining an active physical routine helps mitigate estrogen dominance.
Also Read: What are the Signs and Symptoms of Fibroids?
Frequently Asked Questions (FAQs)
1. Is a bulky uterus a serious or dangerous condition?
A bulky uterus is rarely dangerous or life-threatening. In the vast majority of cases, it is caused by completely benign (non-cancerous) conditions like adenomyosis or fibroids. However, it can significantly compromise your quality of life through severe bleeding, anemia, and pelvic pain, and requires medical attention if you are planning to conceive.
2. What is considered a normal uterus size in millimeters?
In reproductive-aged adult females, a normal uterus measures approximately 70 mm to 80 mm (7 to 8 cm) in length, 40 mm to 50 mm (4 to 5 cm) in width, and 25 mm to 35 mm (2.5 to 3.5 cm) in thickness. A measurement persistently exceeding 85 mm in length or 45 mm in thickness is generally classified as bulky.
3. Can I get pregnant naturally with a bulky uterus?
Yes. Many women with a mildly bulky uterus conceive naturally without medical assistance, particularly when the enlargement is due to past pregnancies or small subserosal fibroids that do not distort the uterine cavity. However, if enlargement is driven by active adenomyosis or cavity-distorting fibroids, consulting a fertility specialist is recommended.
4. Does a bulky uterus cause weight gain or a protruding belly?
A bulky uterus does not cause general body fat accumulation. However, a moderately to severely enlarged uterus can cause noticeable abdominal distension, pelvic fullness, and bloating—often termed a "fibroid belly" or "bulky belly"—making waistbands feel tight and creating the visual appearance of early pregnancy.
5. Can a bulky uterus turn into cancer?
No. Common causes of a bulky uterus, such as adenomyosis and uterine leiomyomas (fibroids), are benign and do not transform into cancer. Very rarely, rapid postmenopausal uterine enlargement can indicate a uterine sarcoma or endometrial carcinoma, which is why postmenopausal bleeding or rapid growth requires prompt evaluation.
6. Can a bulky uterus be cured without surgery?
While medical treatments cannot completely eliminate adenomyosis or make large fibroids disappear permanently, medications such as GnRH agonists, tranexamic acid, and the Mirena IUD can shrink tissue bulk, stop heavy bleeding, and provide near-complete symptom control without surgical removal.
7. How does a bulky uterus affect IVF success rates?
An untreated bulky uterus caused by severe adenomyosis or submucosal fibroids can lower IVF implantation rates and double early pregnancy loss risk due to local inflammation and altered blood flow. However, undergoing 2 to 3 months of GnRH-agonist downregulation (Lupron depot) prior to frozen embryo transfer successfully normalizes success rates.
8. What is the difference between a bulky uterus and adenomyosis?
A bulky uterus is a descriptive ultrasound observation of enlarged dimensions, whereas adenomyosis is a specific medical disease where endometrial lining cells invade the uterine muscle wall. Adenomyosis is one of the most frequent underlying causes of a bulky uterus.
9. When should I see a doctor for a bulky uterus?
You should schedule an evaluation with a gynecologist or fertility specialist if you experience periods lasting longer than 7 days, pass large blood clots, experience severe cramps that disrupt daily life, feel chronic pelvic pressure or urinary frequency, or have been trying to conceive for 6 to 12 months without success.
When to Consult Progenesis Fertility Center
A bulky uterus does not have to dictate your life, rob you of your energy, or end your parenthood dreams. Whether you are struggling with debilitating monthly periods, managing chronic pelvic pressure, or experiencing recurrent implantation failures, accurate diagnostic mapping is the first step toward effective relief.
At Progenesis Fertility Center, our multidisciplinary team of reproductive endocrinologists, gynecological surgeons, and fertility experts utilize state-of-the-art 3D pelvic ultrasound, personalized hormonal protocols, and advanced minimally invasive surgical techniques to restore your uterine health and help you achieve a successful pregnancy.
Take the first step toward clarity and compassionate care today.
👉 Book a Free Fertility Consultation at Progenesis IVF or call our patient care helpline at +91 70309 44041 to discuss your ultrasound findings with our senior specialists.

